
KEY ELIGIBILITY CRITERIA
- Locally advanced or metastatic NSCLC
- Treatment-naïve
- Documented EGFR ex19del or L858R
- ECOG PS 0 or 1

Overall Survival – Secondary Endpoint
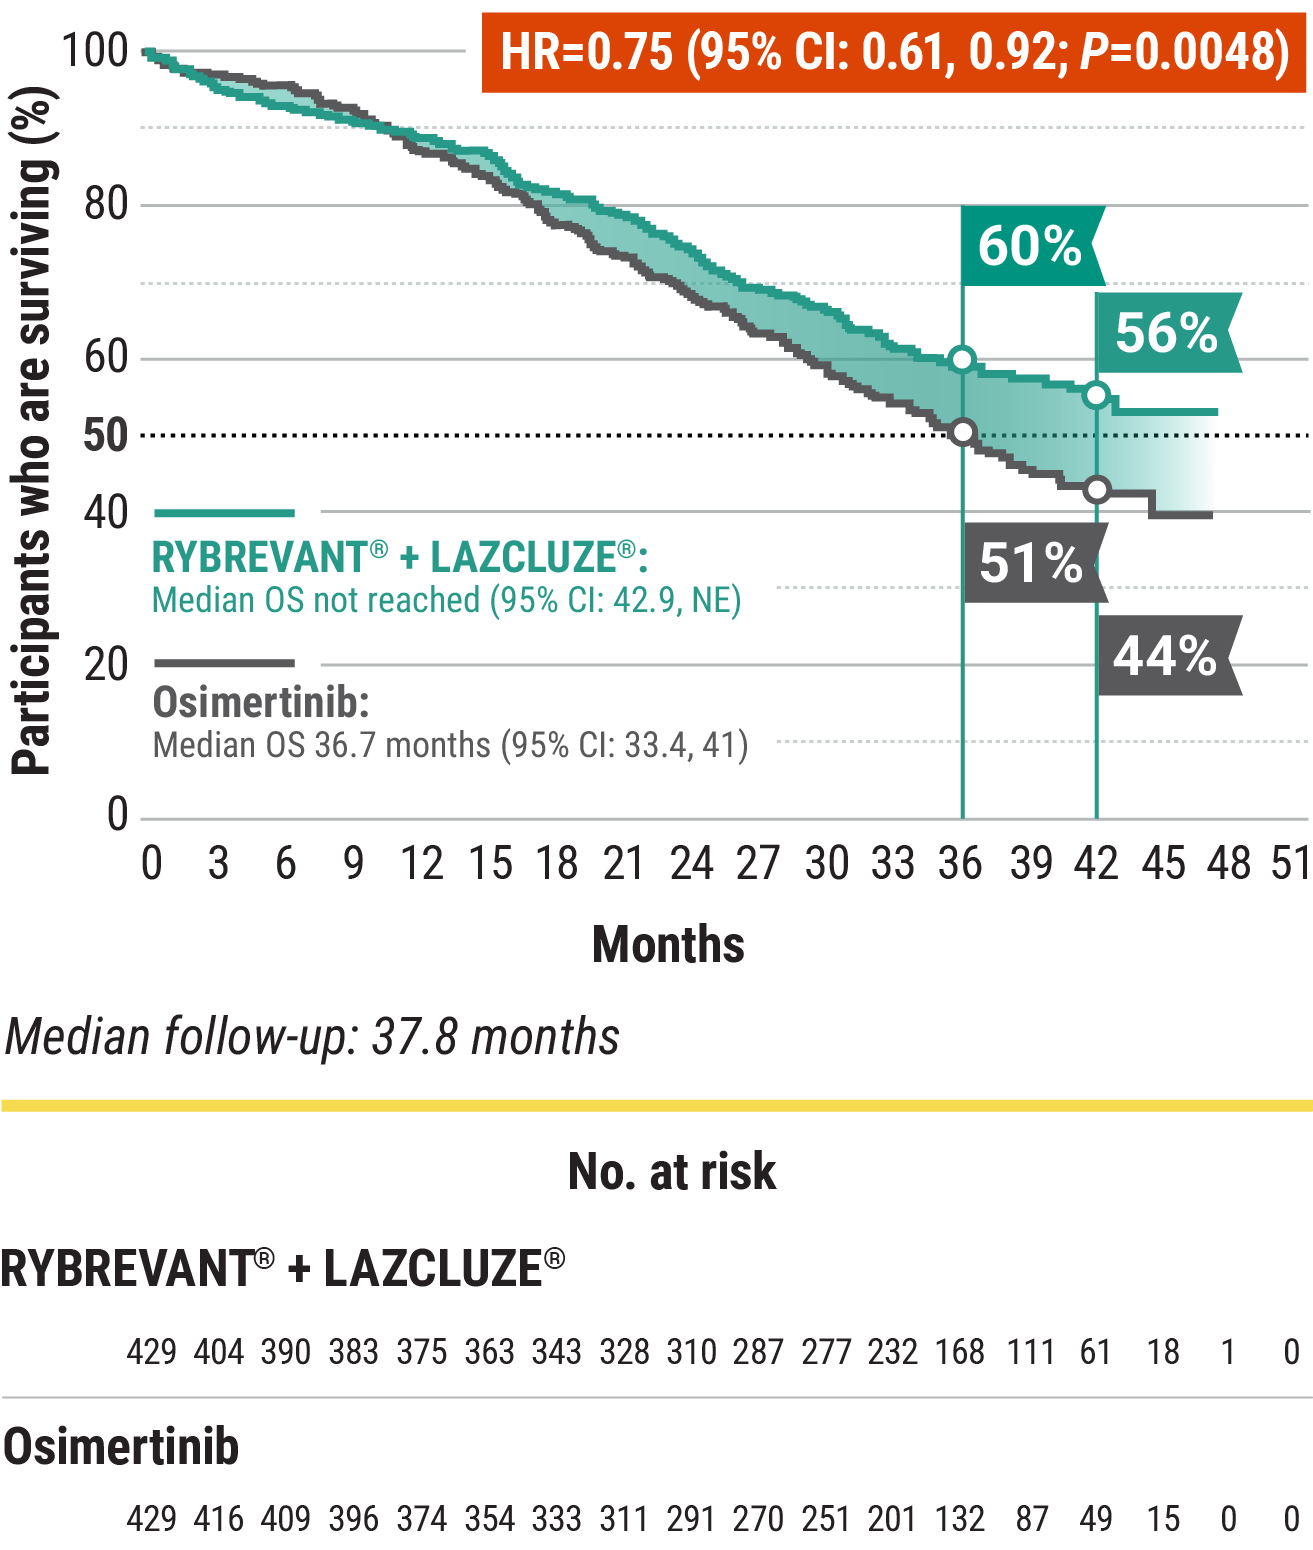
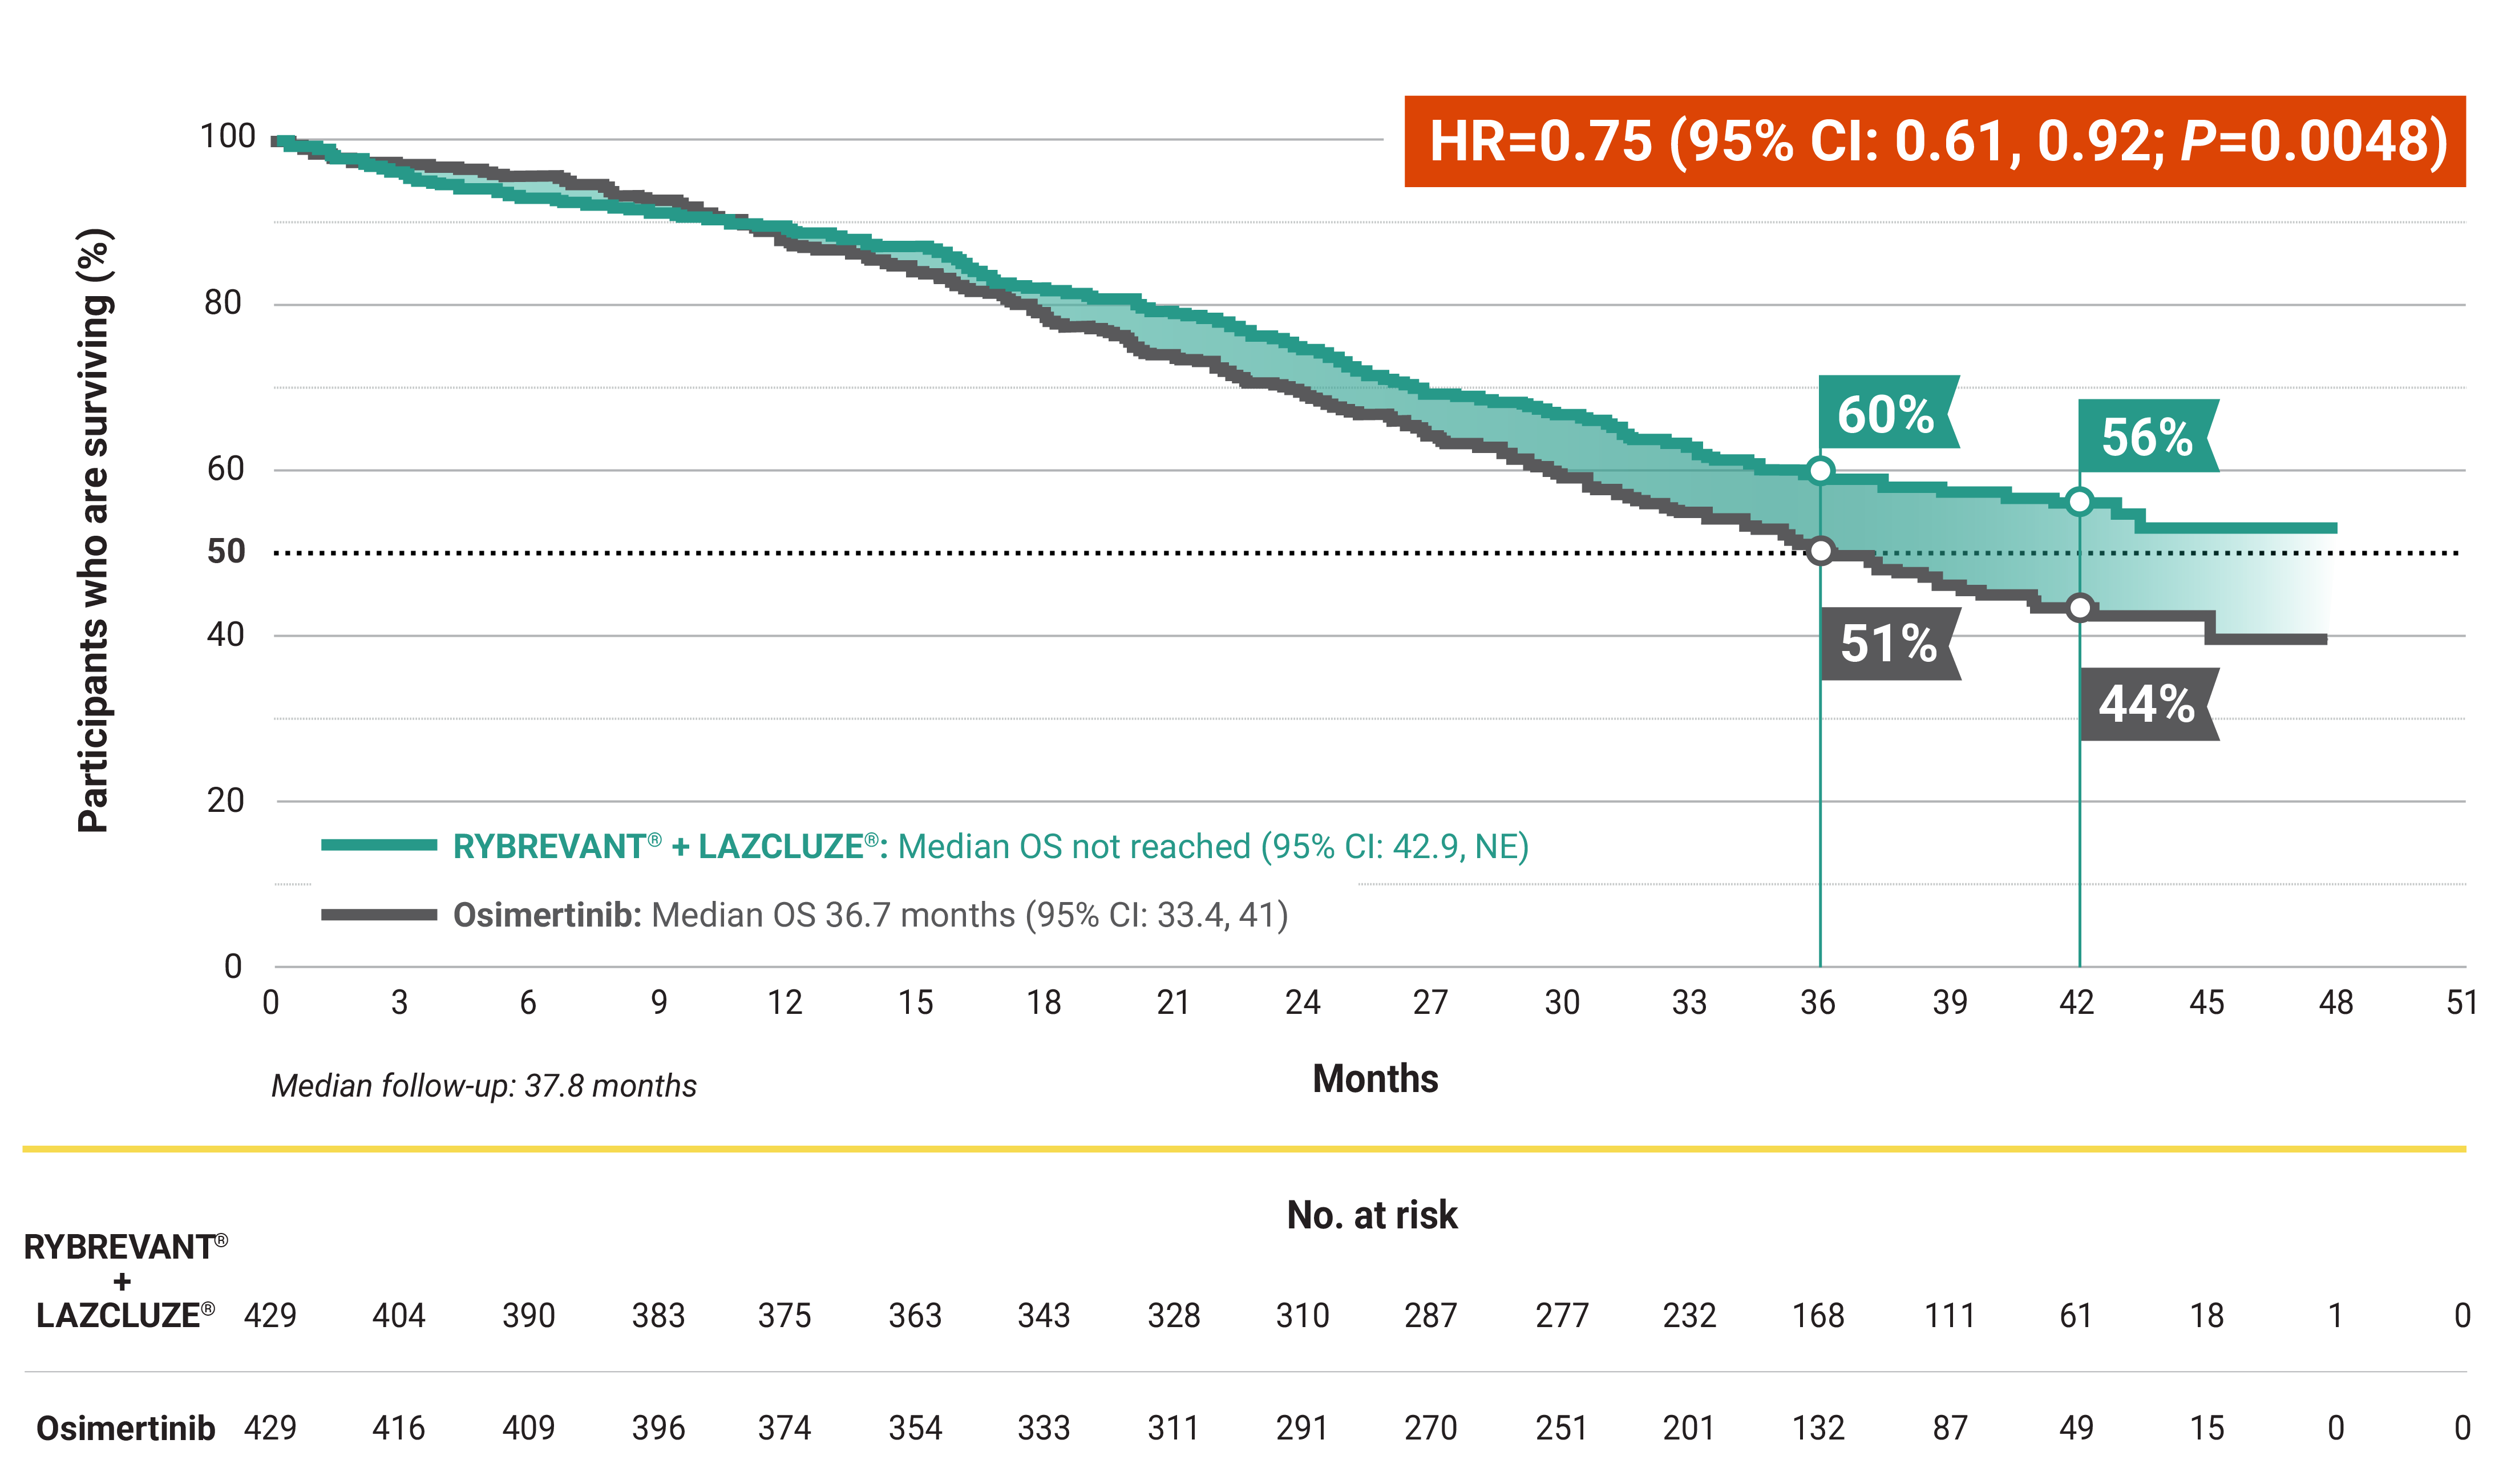
Based on modeling using observed HR and mOS in the osimertinib group, assuming exponential distribution of OS in both arms. The baseline factors were: mutation type, race, brain metastases, age, sex, ECOG PS, and weight. This is a conservative estimate; final results may vary.3
CI, confidence interval; ECOG PS, Eastern Cooperative Oncology Group performance status; EGFR, epidermal growth factor receptor; HR, hazard ratio; mNSCLC, metastatic non–small cell lung cancer; mOS, median overall survival; NE, not estimable; NSCLC, non–small cell lung cancer; OS, overall survival.
Progression-Free Survival – Primary Endpoint
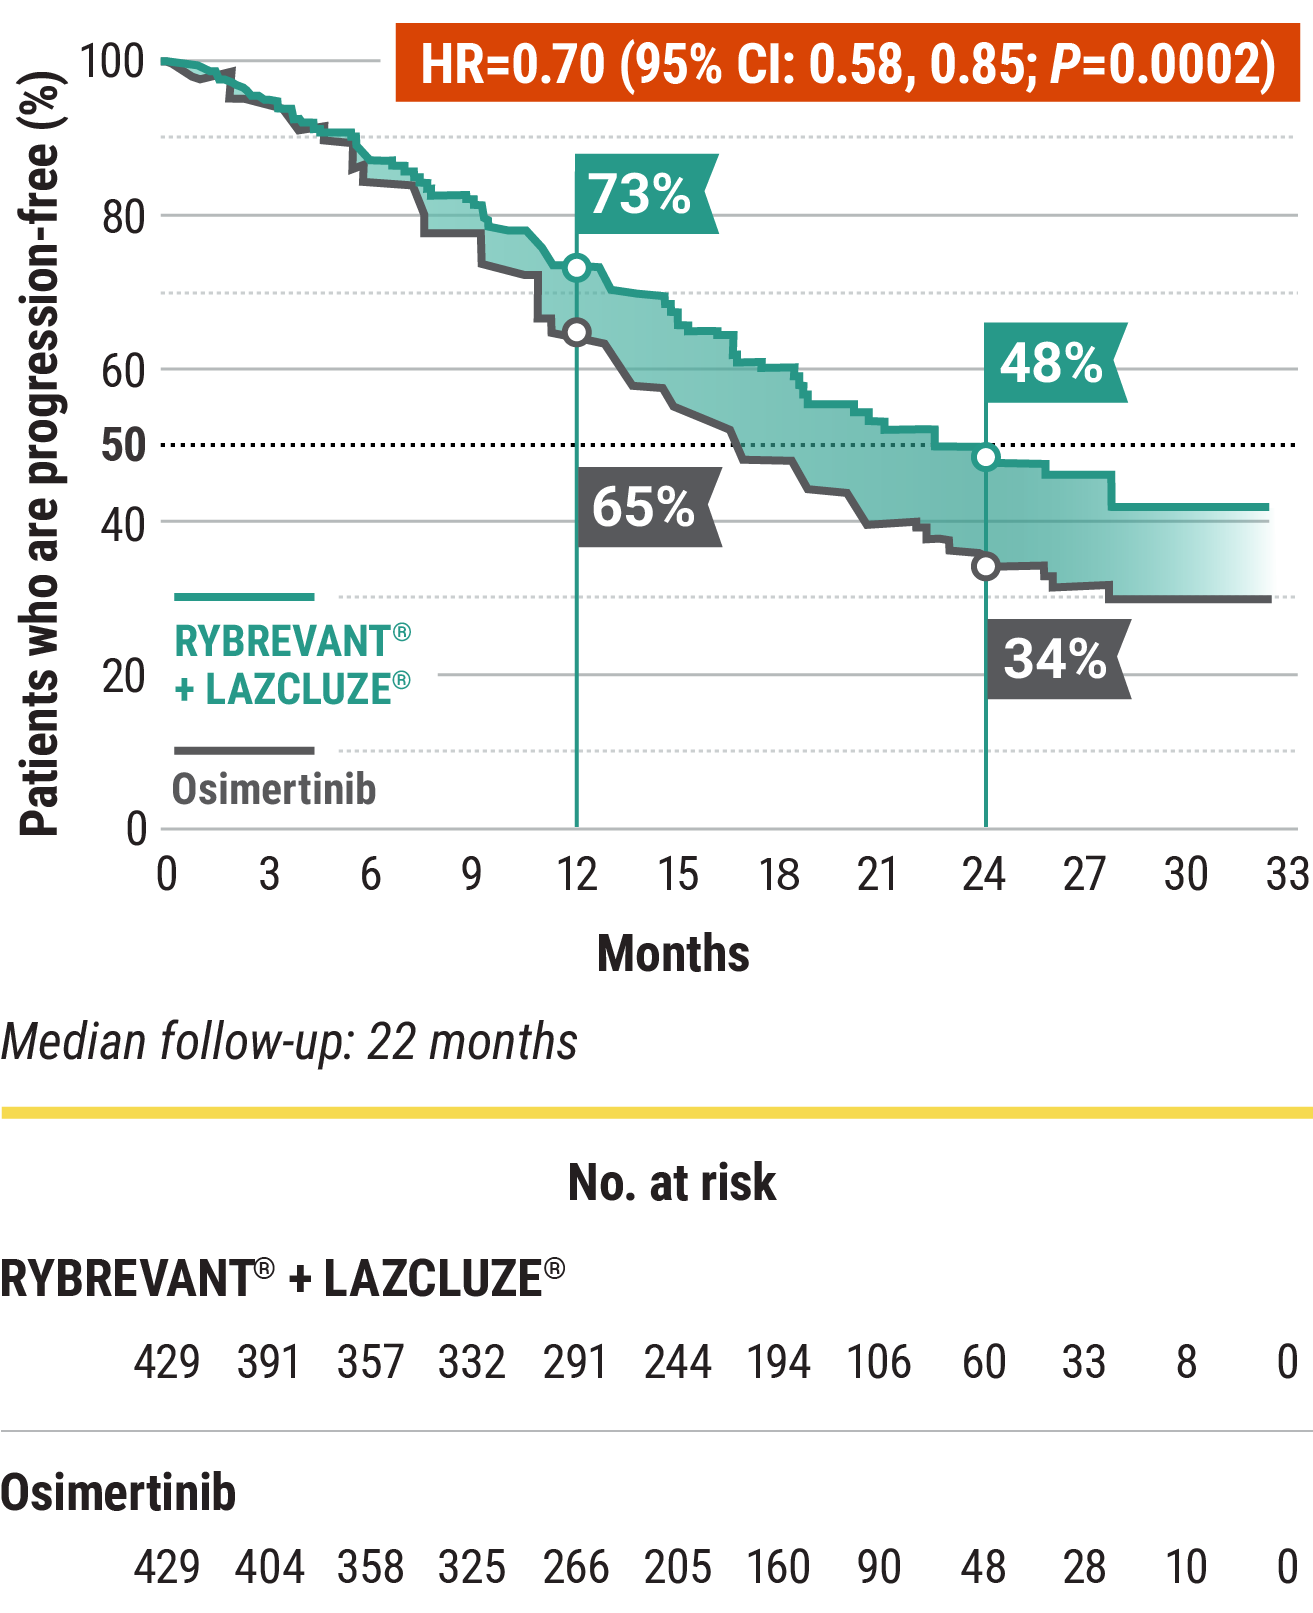
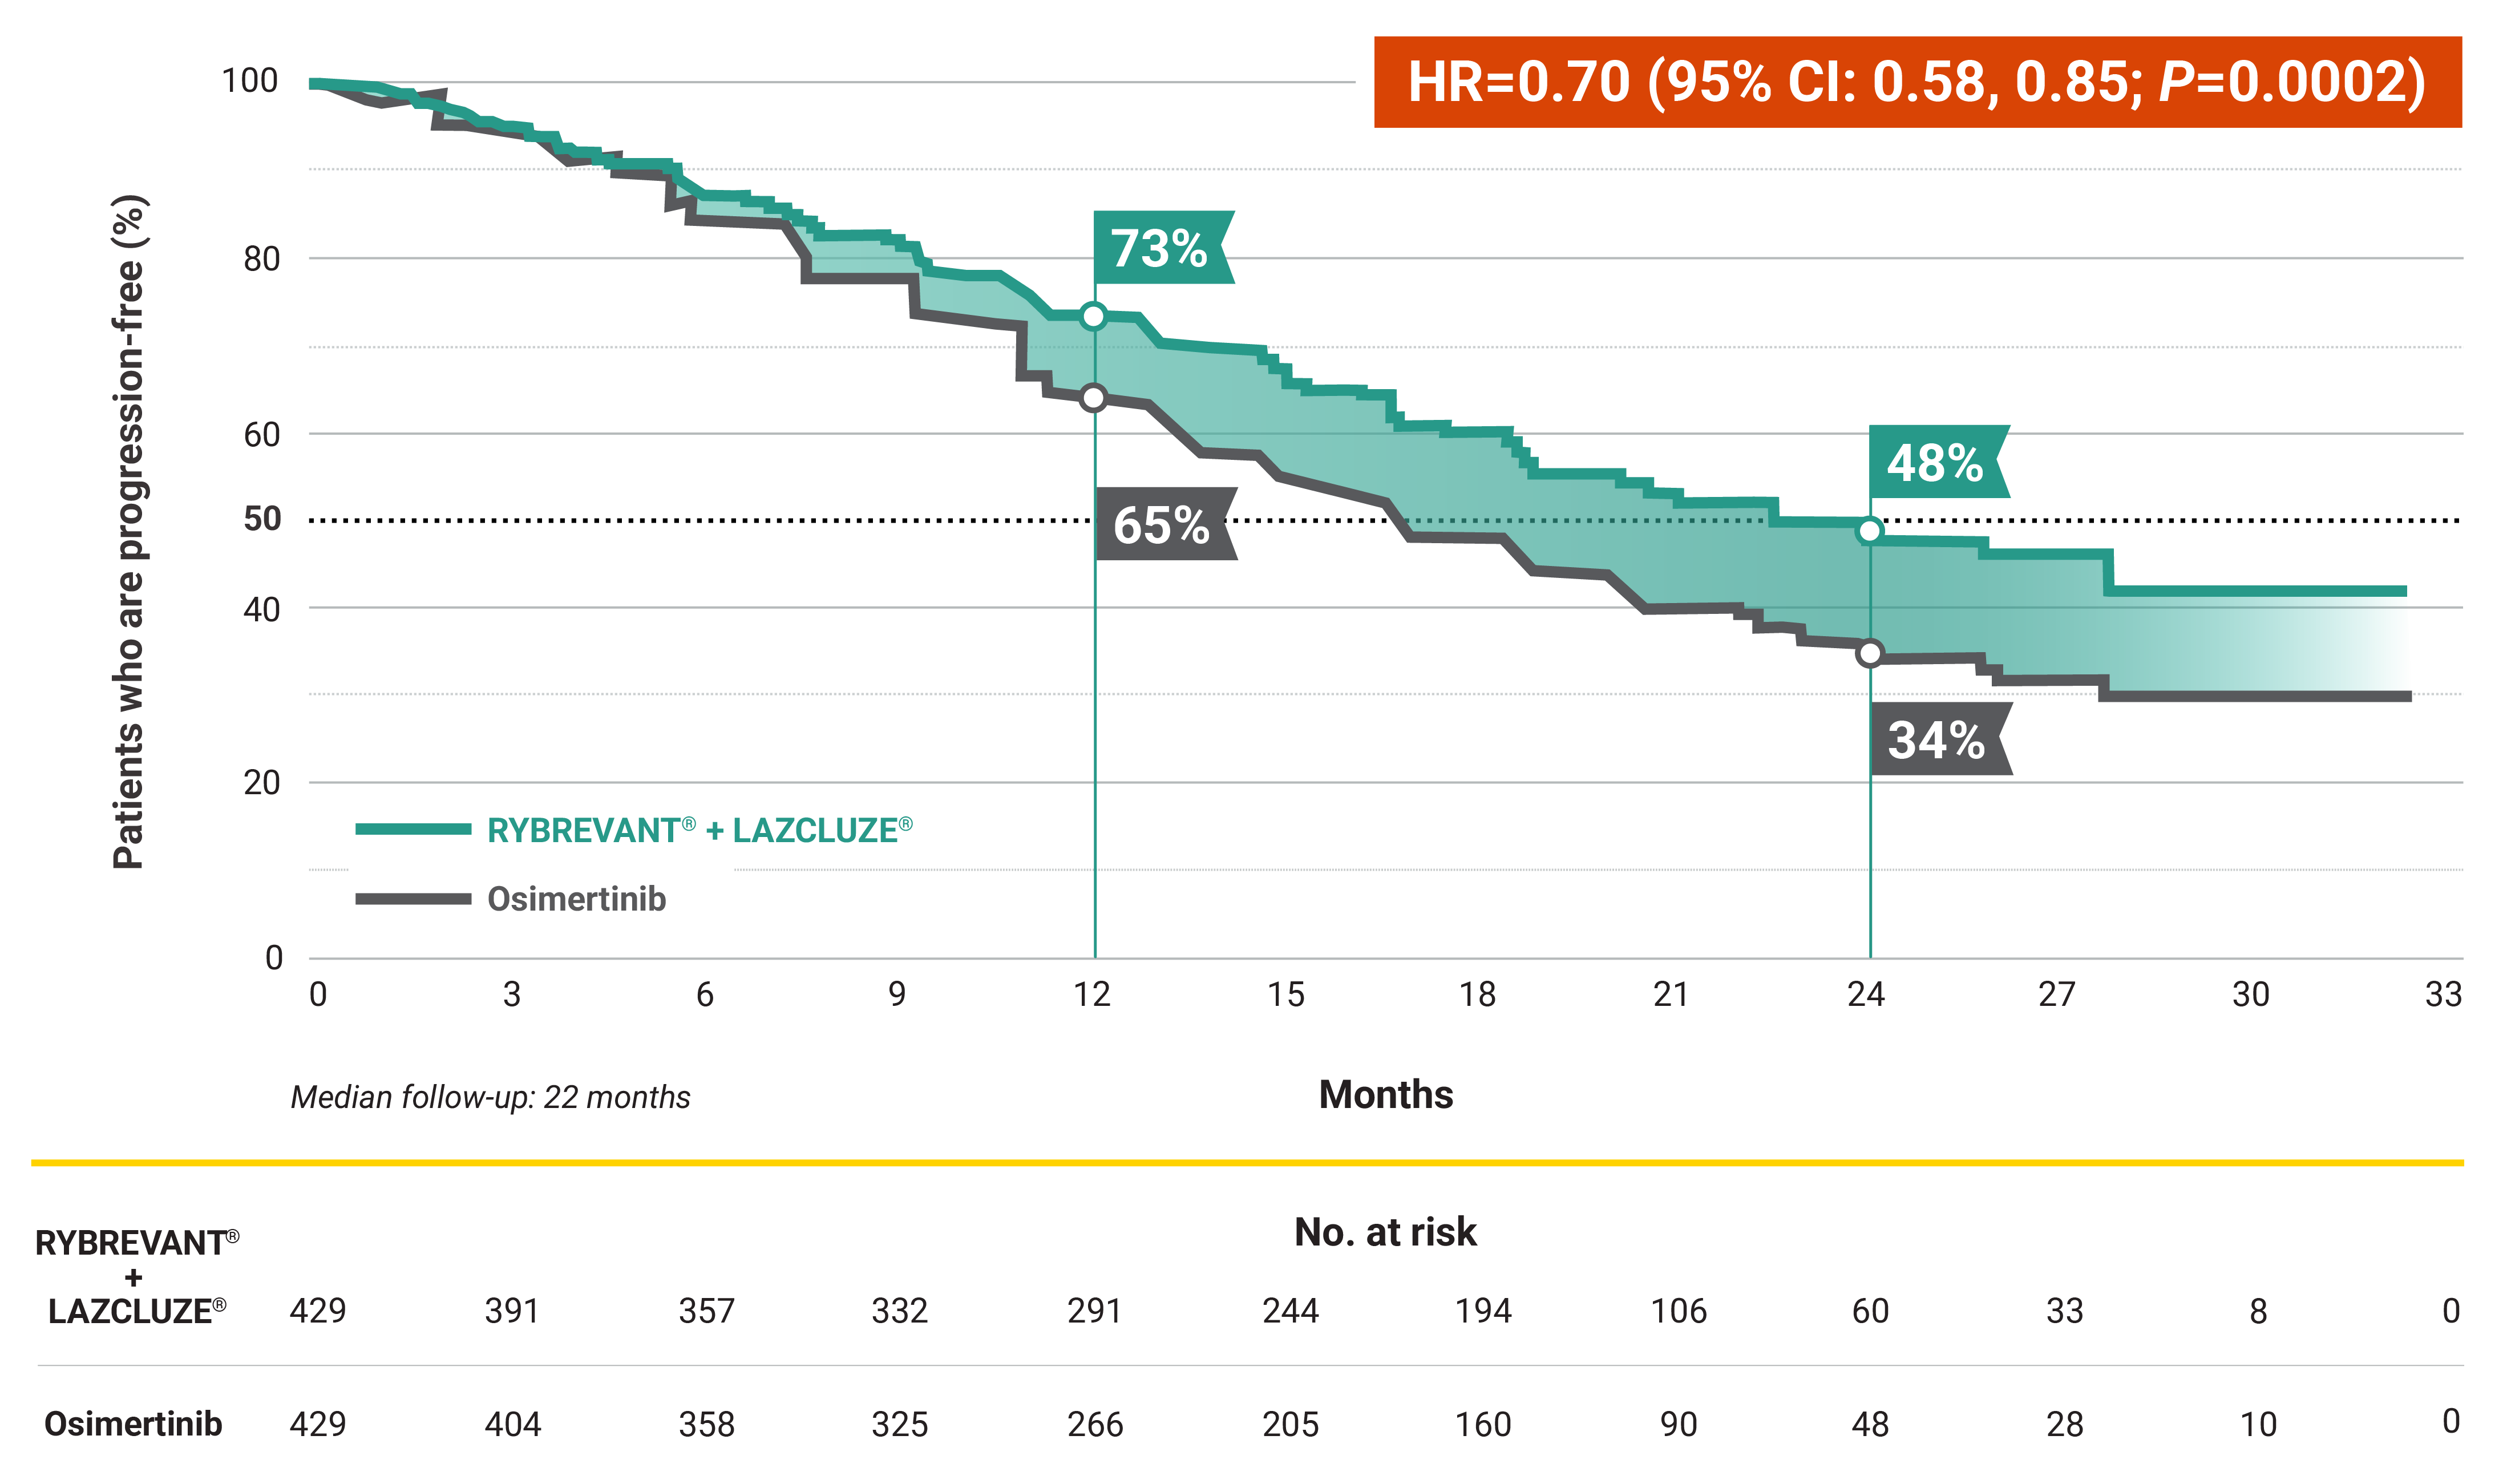
*EGFR mutation discovered prior to first-line systemic therapy.6
†Amivantamab includes both amivantamab and hyaluronidase-lpuj (RYBREVANT FASPRO™) subcutaneous injection and IV amivantamb-vmjw (RYBREVANT®). Amivantamab and hyaluronidase-lpuj has different dosing and administration instructions compared with IV amivantamab-vmjw.6
‡EGFR exon 19 deletion or exon 21 L858R mutations.6
§See the NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) for detailed recommendations, including other treatment options.
||Prophylactic anticoagulation is recommended at the time of initiation to prevent venous thromboembolic events.6
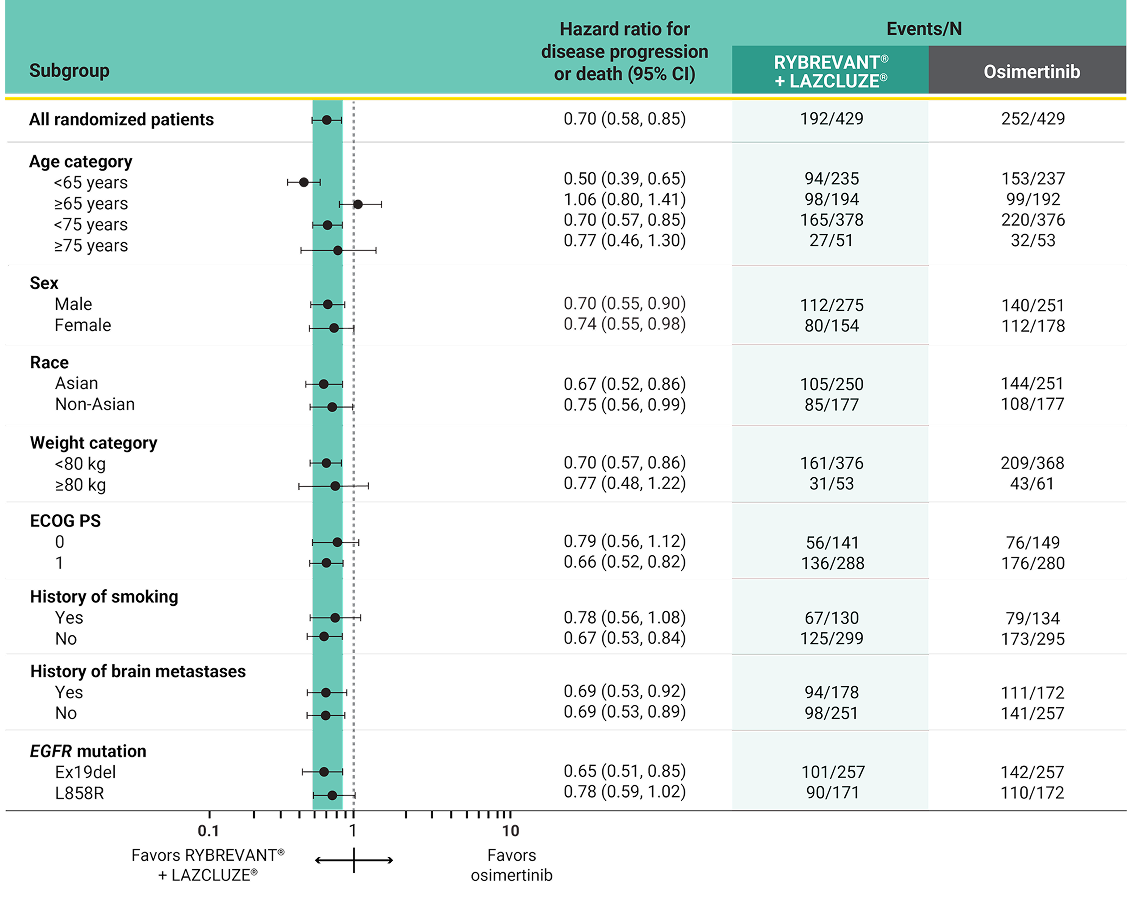
PFS results in prespecified subgroups5

Pathogenic alterations (N=636) were identified by NGS using ctDNA from blood with Guardant360 CDx at baseline18

Other common high-risk features included5,18:
41%
brain metastases
(RYBREVANT® + LAZCLUZE® N=178, osimertinib N=172)
16%
liver metastases
(RYBREVANT® + LAZCLUZE® N=64, osimertinib N=72)
85%
detectable ctDNA
(RYBREVANT® + LAZCLUZE® N=231, osimertinib N=240)
Brain metastases | Liver metastases | TP53 co-mutation | ctDNA by ddPCR† | |||||
|---|---|---|---|---|---|---|---|---|
RYBREVANT® (N=178)+ LAZCLUZE® | Osimertinib (N=172) | RYBREVANT® (N=64)+ LAZCLUZE® | Osimertinib (N=72) | RYBREVANT® (N=149)+ LAZCLUZE® | Osimertinib (N=144) | RYBREVANT® (N=231)+ LAZCLUZE® | Osimertinib (N=240) | |
| mPFS, months (95% CI) | 18.3 (16.6, 23.7) | 13 (12.2, 16.4) | 18.2 (13.1, NE) | 11 (7.4, 12.8) | 18.2 (15.3, 22.1) | 12.9 (11.1, 14.7) | 20.3 (16.6, 24) | 14.8 (12.9, 16.5) |
| HR (95% CI) | 0.69 (0.53, 0.92) | 0.58 (0.37, 0.91) | 0.65 (0.48, 0.87) | 0.68 (0.53, 0.86) | ||||
| Reduction in risk of progression or death | 31% | 42% | 35% | 32% | ||||
RYBREVANT® (N=178)+ LAZCLUZE® | 18.3 (16.6, 23.7) | 0.69 (0.53, 0.92) | 31% |
Osimertinib (N=172) | 13 (12.2, 16.4) |
RYBREVANT® (N=64)+ LAZCLUZE® | 18.2 (13.1, NE) | 0.58 (0.37, 0.91) | 42% |
Osimertinib (N=72) | 11 (7.4, 12.8) |
RYBREVANT® (N=149)+ LAZCLUZE® | 18.2 (15.3, 22.1) | 0.65 (0.48, 0.87) | 35% |
Osimertinib (N=144) | 12.9 (11.1, 14.7) |
RYBREVANT® (N=231)+ LAZCLUZE® | 20.3 (16.6, 24) | 0.68 (0.53, 0.86) | 32% |
Osimertinib (N=240) | 14.8 (12.9, 16.5) |
This analysis is not included in the Prescribing Information for RYBREVANT® or LAZCLUZE®. This was a post hoc exploratory analysis and was not powered to show statistical significance.
*In MARIPOSA, pathogenic alterations were identified by NGS using ctDNA from blood with Guardant360 CDx at baseline. Ex19del and L858R ctDNA in blood was analyzed at baseline with Biodesix ddPCR. This exploratory analysis included all randomized patients who had 1 or more biomarker assessments. Subgroup analyses of efficacy endpoints were carried out using statistical methods for the primary analysis of the general MARIPOSA population.18
†Consistent results were seen in patients with detectable ctDNA using NGS (HR=0.71 [95% CI: 0.57, 0.89]).18
28%

reduction in risk of death
HR=0.72
(95% CI: 0.53, 0.97)
RYBREVANT® + LAZCLUZE® n=149, osimertinib n=144
18.2-month mPFS with RYBREVANT® + LAZCLUZE® and 12.9-month mPFS with osimertinib
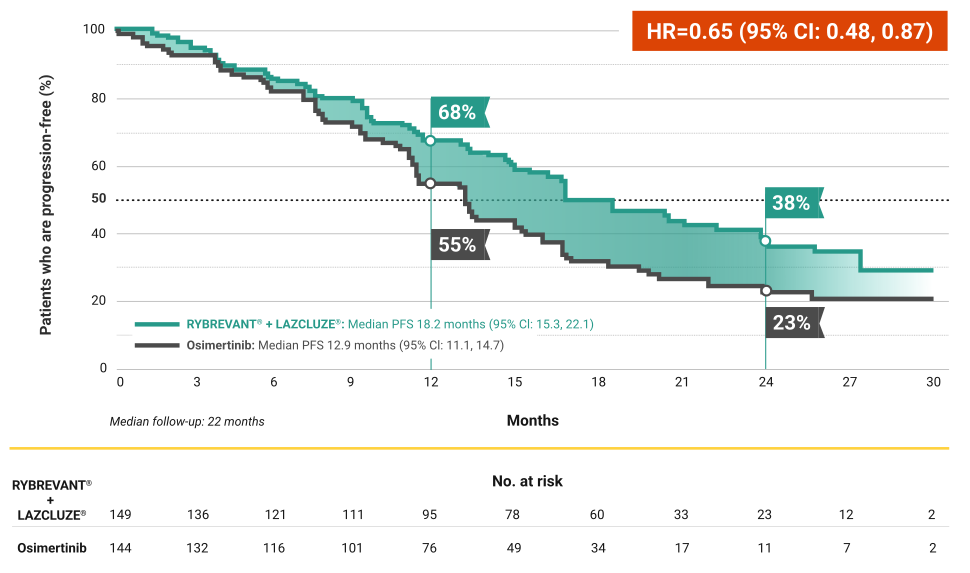
35%
reduction in risk of progression or death
These analyses are not included in the Prescribing Information for RYBREVANT® or LAZCLUZE®.
These were post hoc exploratory analyses and were not powered to show statistical significance.
1L, first-line; ctDNA, circulating tumor DNA; ddPCR, droplet digital polymerase chain reaction; DNA, deoxyribonucleic acid; ex19del, exon 19 deletion; IV, intravenous; mPFS, median progression-free survival; NGS, next-generation sequencing; PFS, progression-free survival; TP53, tumor protein p53.
This was a prespecified analysis and was not powered to show statistical significance.
Median duration of response


This was a prespecified analysis and was not powered to show statistical significance.
CR, complete response; mDOR, median duration of response; ORR, overall response rate; PR, partial response.
CNS Data
Overall survival in patients with history of brain metastases3
(95% CI: 0.5, 0.9)
RYBREVANT® + LAZCLUZE® n=178, osimertinib n=173
Patients with a history of brain metastases were eligible to enroll in the study (RYBREVANT® + LAZCLUZE® n=180, osimertinib n=186).3
Patients with untreated symptomatic brain metastases and active or prior leptomeningeal disease were excluded from the study.30
This was a prespecified secondary analysis and was not powered to show statistical significance.
Intracranial PFS|| at 36 months in patients with intracranial lesions at baseline3


This was a prespecified secondary analysis and was not powered to show statistical significance.
*Amivantamab includes both amivantamab and hyaluronidase-lpuj (RYBREVANT FASPRO™) subcutaneous injection and IV amivantamab-vmjw (RYBREVANT®). Amivantamab and hyaluronidase-lpuj has different dosing and administration instructions compared with IV amivantamab-vmjw.29
†Including but not limited to amivantamab-vmjw + lazertinib.29
‡EGFR exon 19 deletion or exon 21 L858R mutations.29
§See the NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) for detailed recommendations, including other treatment options.
||Based on median follow-up of 37.8 months.3
This was a prespecified exploratory analysis and was not powered to show statistical significance.
Median intracranial duration of response
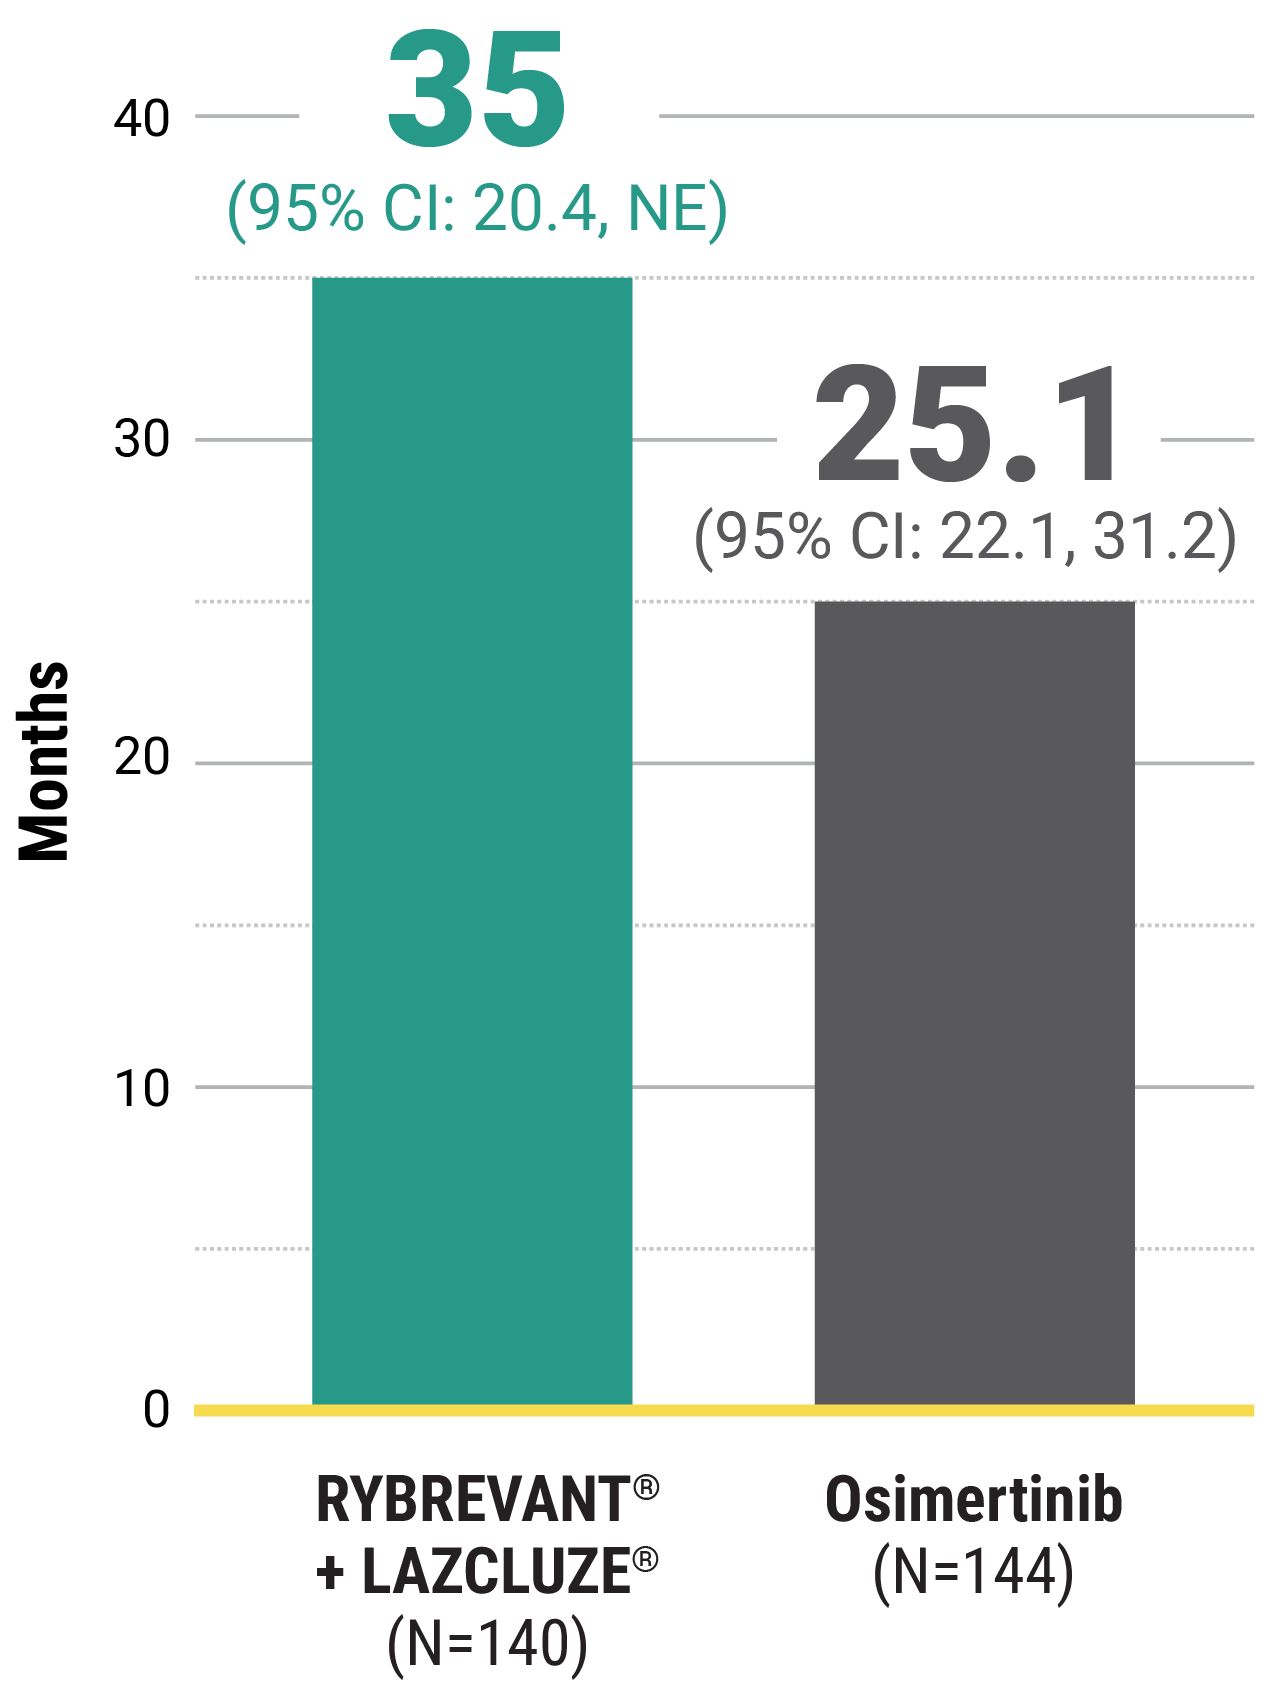
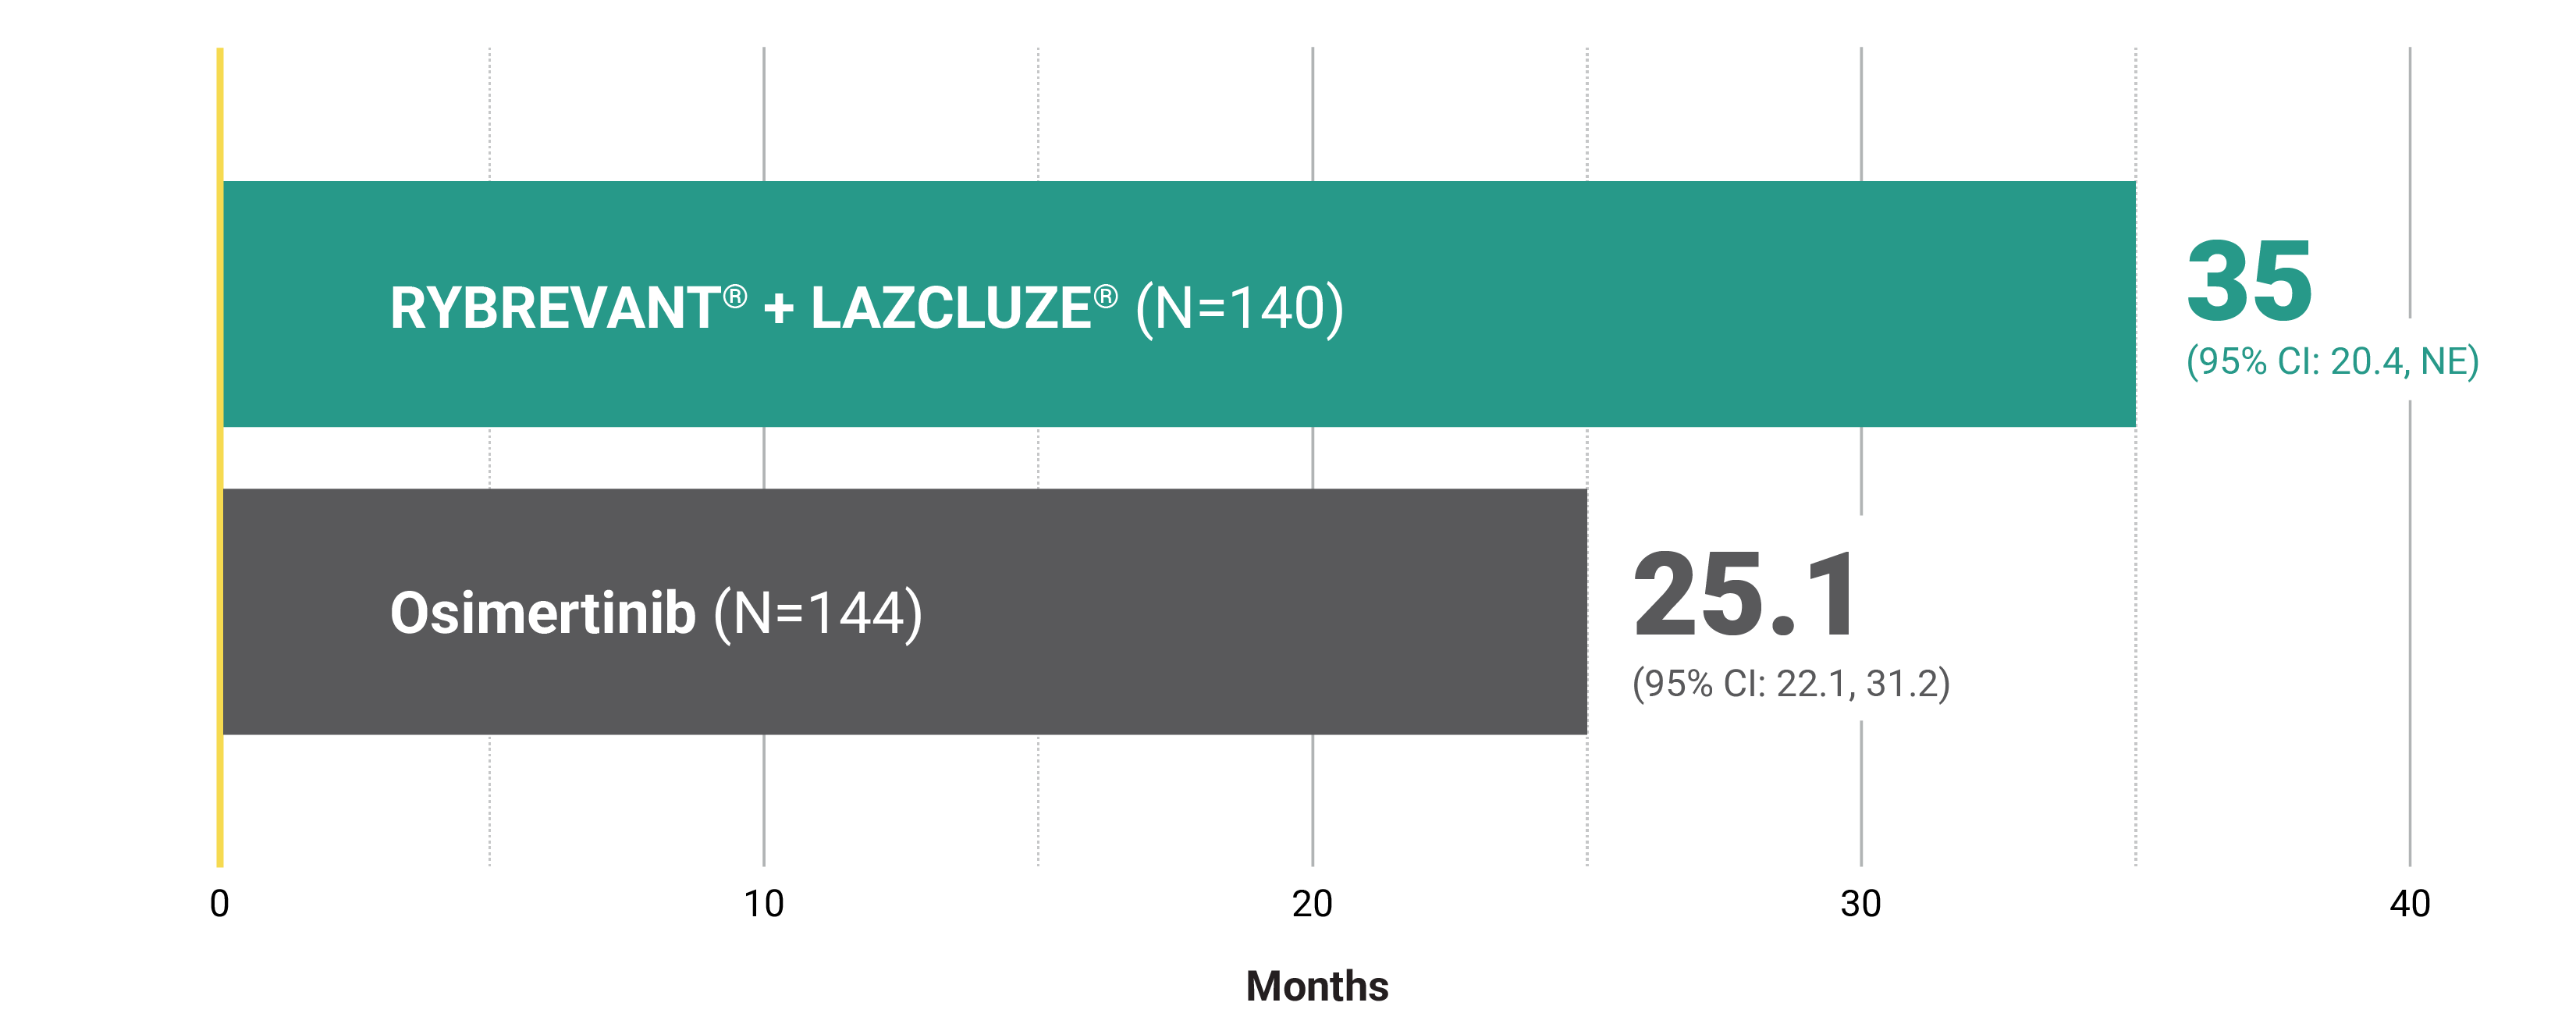
This was a prespecified exploratory analysis and was not powered to show statistical significance.
*Based on median follow-up of 37.8 months.3
†Based on subgroup of subjects with history of brain metastasis. CR and PR do not have to be confirmed.27
‡Amivantamab includes both amivantamab and hyaluronidase-lpuj (RYBREVANT FASPRO™) subcutaneous injection and IV amivantamab-vmjw (RYBREVANT®). Amivantamab and hyaluronidase-lpuj has different dosing and administration instructions compared with IV amivantamab-vmjw.29
§Including but not limited to amivantamab + lazertinib.29
||EGFR exon 19 deletion or exon 21 L858R mutations.29
¶See the NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) for detailed recommendations, including other treatment options.
CNS, central nervous system; DOR, duration of response.
Study Design
MARIPOSA is an active-controlled, multicenter, phase 3 trial. Patients with asymptomatic or previously treated and stable intracranial metastases were eligible to enroll. Patients received treatment until disease progression or unacceptable toxicity. The evaluation of efficacy relied upon comparison between RYBREVANT® in combination with LAZCLUZE®, and osimertinib.1,5
Serial brain MRIs were conducted on all patients to assess intracranial progression and response5
The largest phase 3 trial and the only one that required serial brain MRIs for all patients, providing accurate detection of CNS progression in patients with 1L EGFR+ disease5,7-17,23*
RANDOMIZATION (N=1,074)
RYBREVANT®
+ LAZCLUZE®
(n=429; open-label)
Osimertinib
(n=429; blinded)
Non-registrational data set
LAZCLUZE®
(n=216; blinded)
RANDOMIZATION (N=1,074)
RYBREVANT®
+ LAZCLUZE®
(n=429; open-label)
Osimertinib
(n=429; blinded)
Non-registrational data set
LAZCLUZE®
(n=216; blinded)
LAZCLUZE® monotherapy arm was included to assess the contribution of the components.5
*MARIPOSA is the largest phase 3 trial that evaluated 1L treatment in patients with EGFR+ mNSCLC as of April 2025.5,7-17
Baseline characteristics were well-balanced across treatment types5
*Other includes American Indian or Alaska Native, Black, Native Hawaiian or Pacific Islander, multiple, and unknown.
†One patient in the RYBREVANT® + LAZCLUZE® arm had both ex19del and L858R.
BICR, blinded independent central review; MRI, magnetic resonance imaging; RECIST, Response Evaluation Criteria in Solid Tumors.
Safety
ARs (≥10%) in patients in MARIPOSA1
*Grouped terms.
†Applicable for RYBREVANT® only.
Select laboratory abnormalities that worsened from baseline (≥20%) in MARIPOSA1*
*The denominator used to calculate the rate is the number of patients with a baseline value and at least one post-treatment value for the specific lab test.
The most common grade 3 or 4 laboratory abnormalities (≥2%) were decreased albumin, decreased sodium, increased alanine aminotransferase, decreased potassium, decreased hemoglobin, increased aspartate aminotransferase, increased gamma-glutamyl transferase, and increased magnesium.1


This was a post hoc exploratory analysis and is not included in the Prescribing Information for RYBREVANT® or LAZCLUZE®.
*Patients with PFS events or who were censored in the first 4 months were excluded from this analysis.
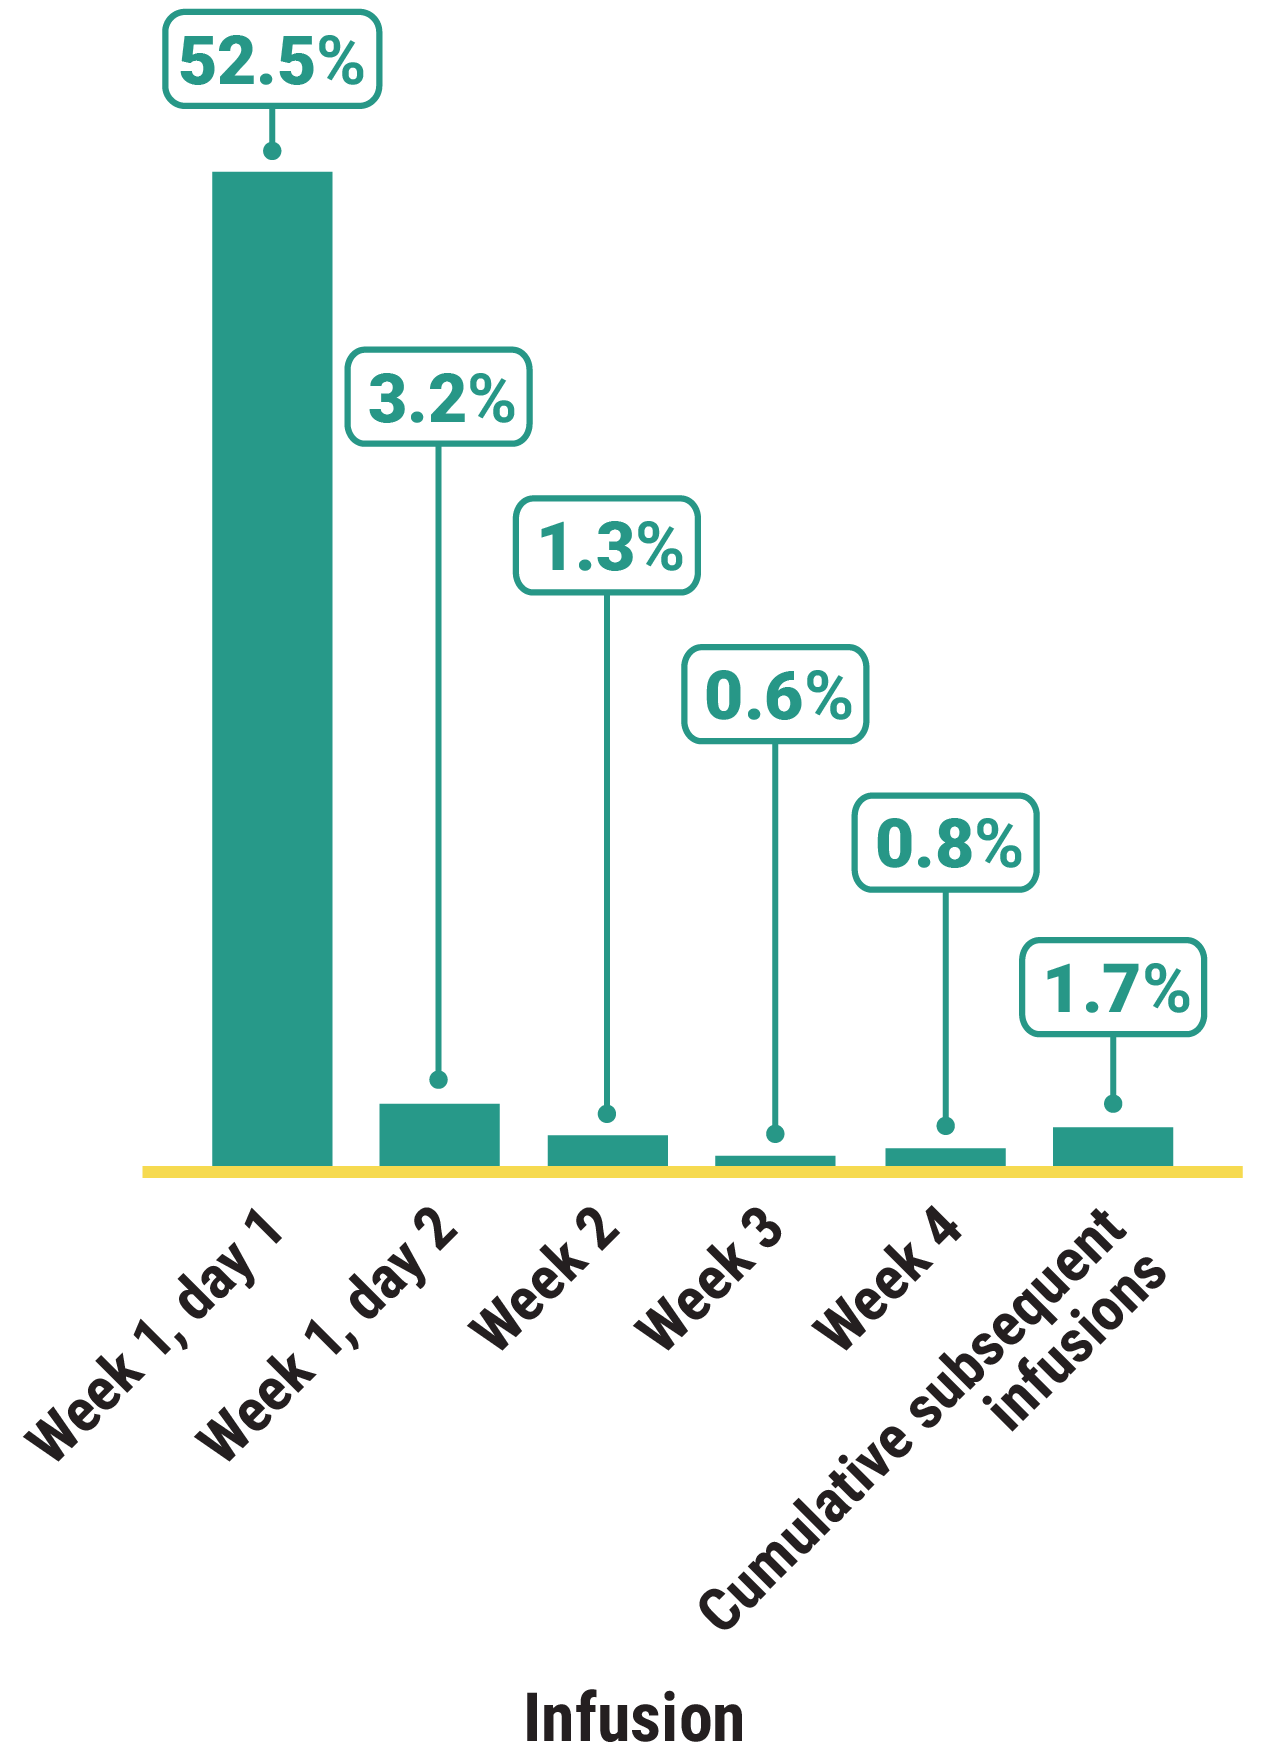
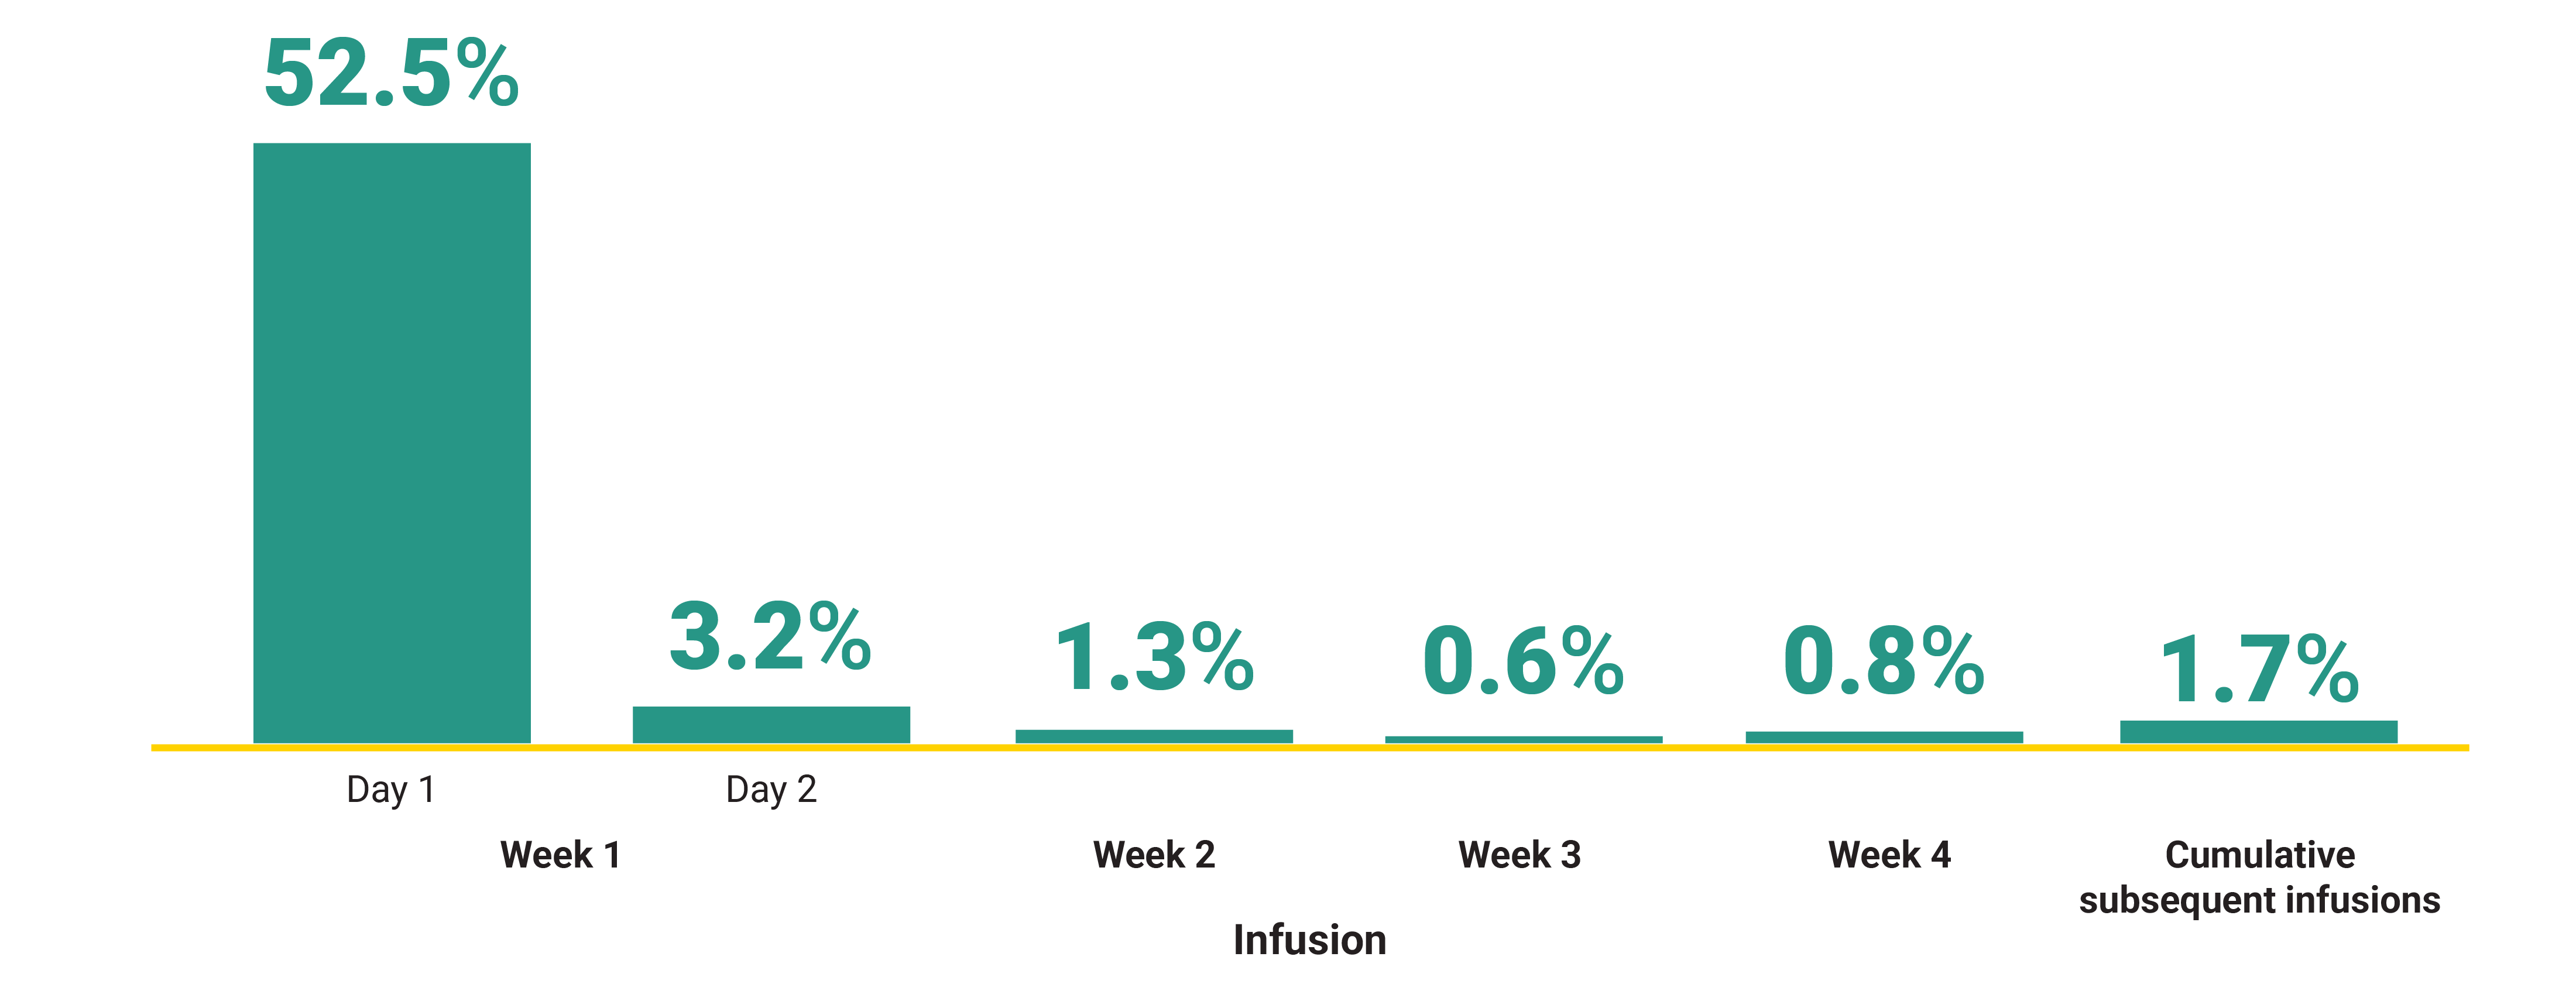
AR, adverse reaction; ILD, interstitial lung disease; IRR, infusion-related reaction; VTE, venous thromboembolism.
Dose Modifications and Discontinuation Rates
Median duration of treatment including dose modifications3
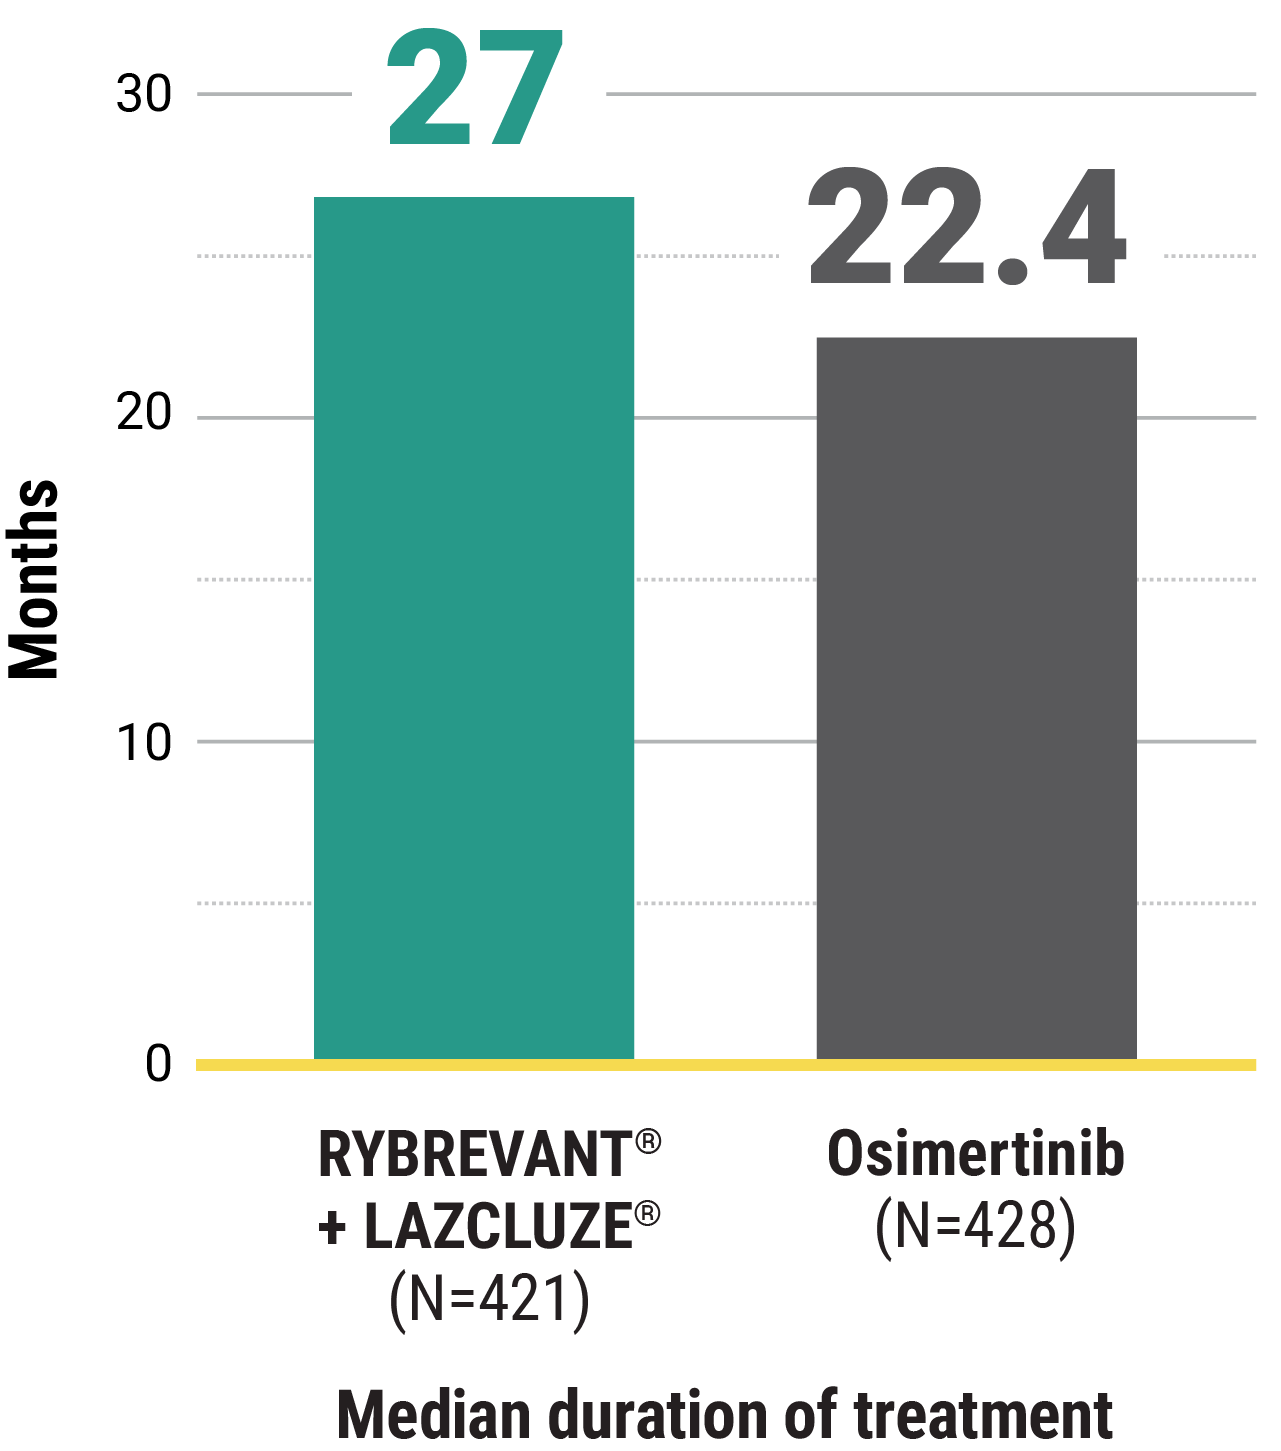
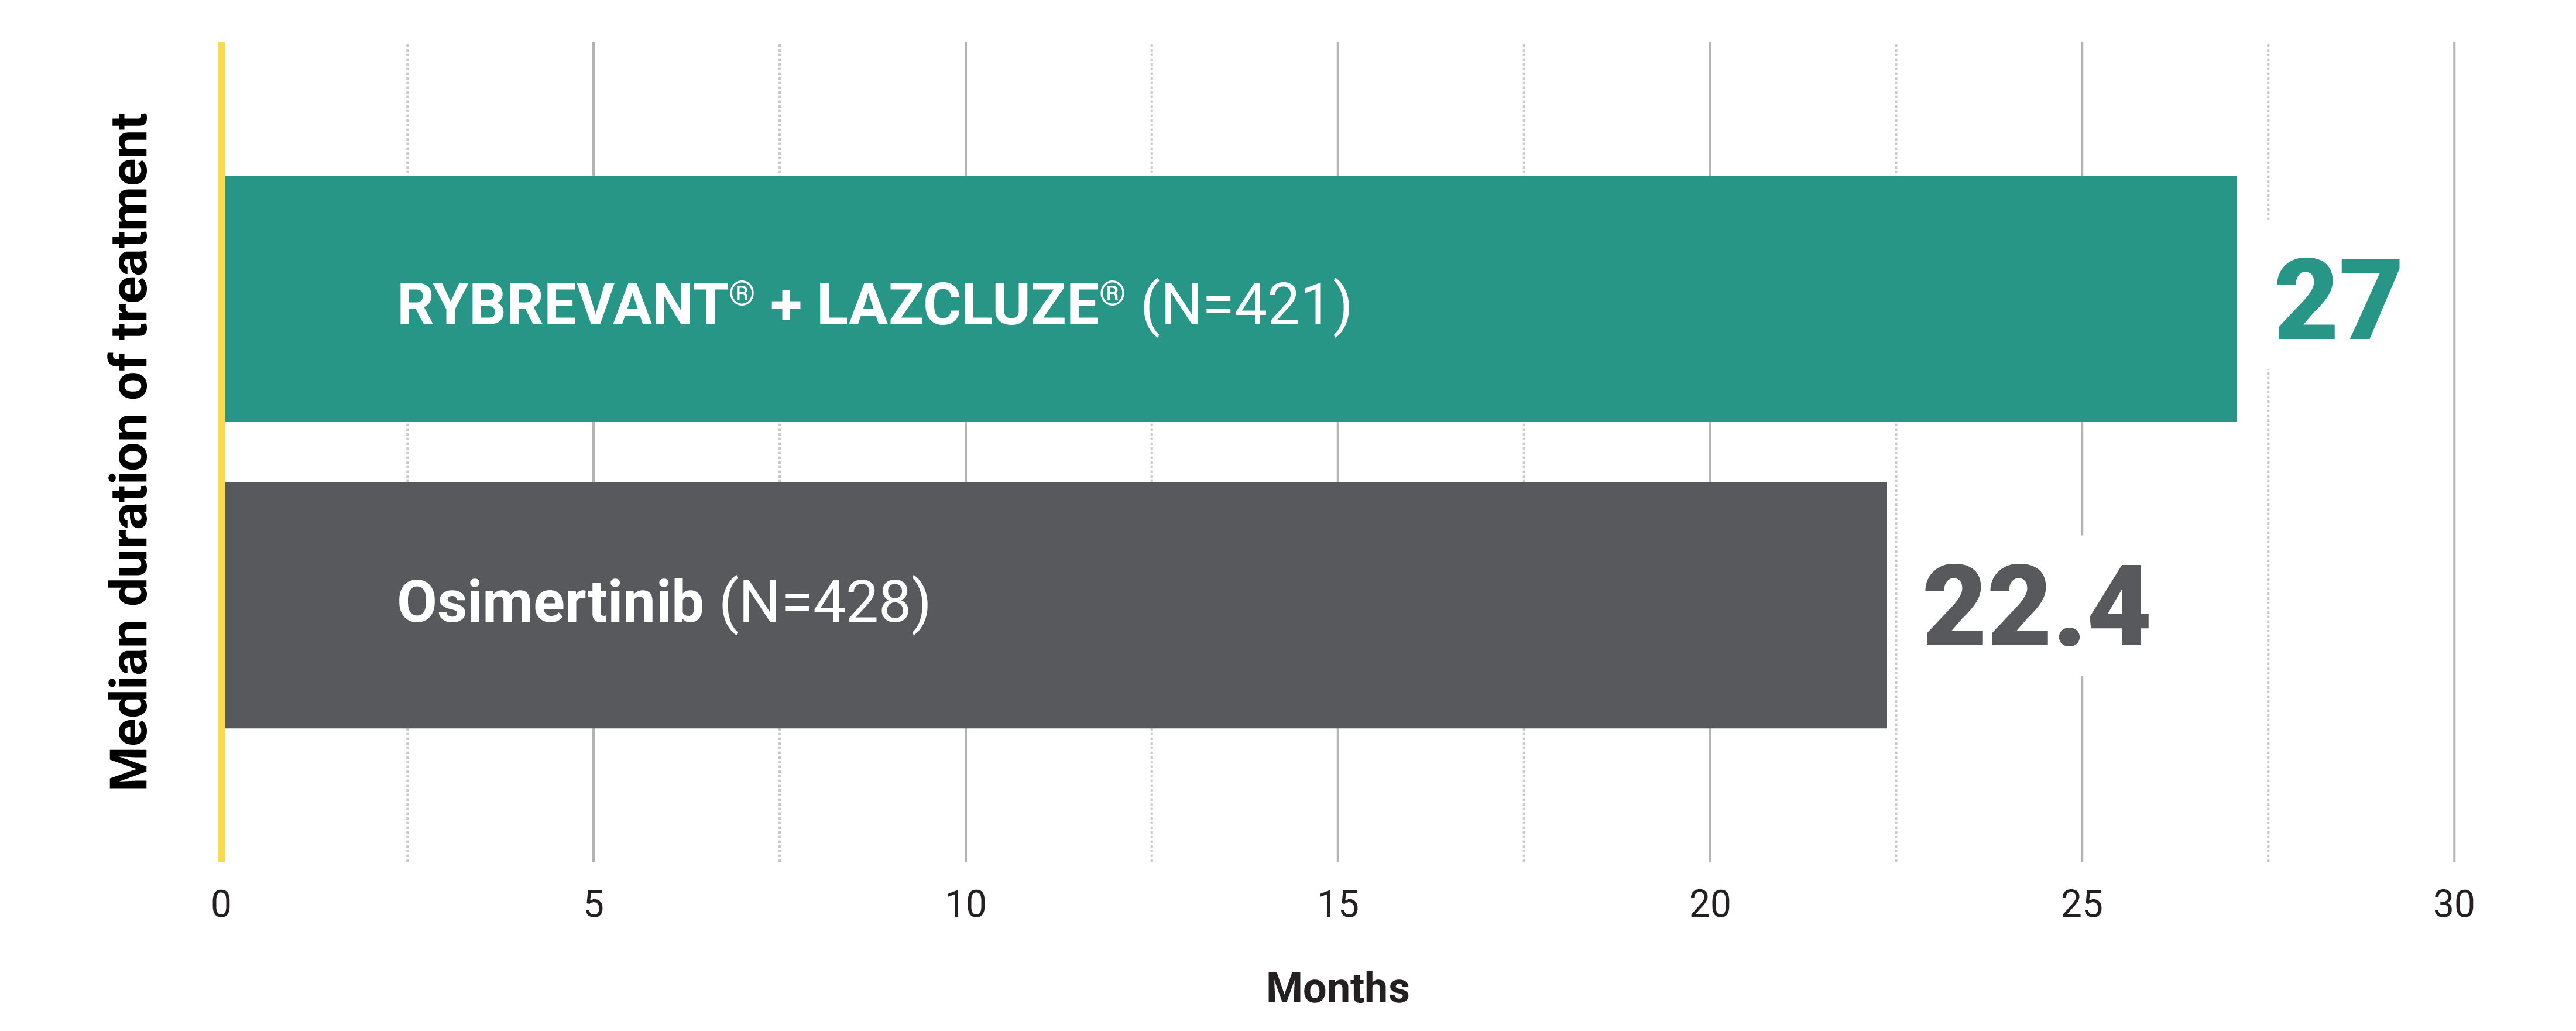
*Certain types and severity of ARs require discontinuation after first occurrence.1
With dose interruptions in the first 4 months:
27.5 months
(95% Cl: 20.3, NE) (N=188)
Without dose interruptions in the first 4 months:
25.7 months
(95% Cl: 22.2, NE) (N=190)
This was a post hoc exploratory analysis from MARIPOSA and is not included in the Prescribing Information for RYBREVANT® or LAZCLUZE®.
*In this descriptive analysis of PFS, the hazard ratio by multivariable analysis (via multivariate Cox proportional hazards model, only included patients still at risk of PFS at 4 months) adjusted for age, ECOG PS, EGFR mutation type, Asian race, and history of brain metastases was 1.06 (95% CI: 0.73, 1.44).32
†To minimize bias, outcomes (such as progression events or deaths that could occur before interruptions leading to outcomes-based selection bias) were evaluated after the first 4 months. Patients who discontinued the study, had disease progression, or died in the first 4 months were not evaluated, as they were not in the study by the cutoff timepoint (and the outcome event may have occurred prior to the interruption).32
Dose modifications1,4
Discontinuation rates
2L, second-line.
References:

